

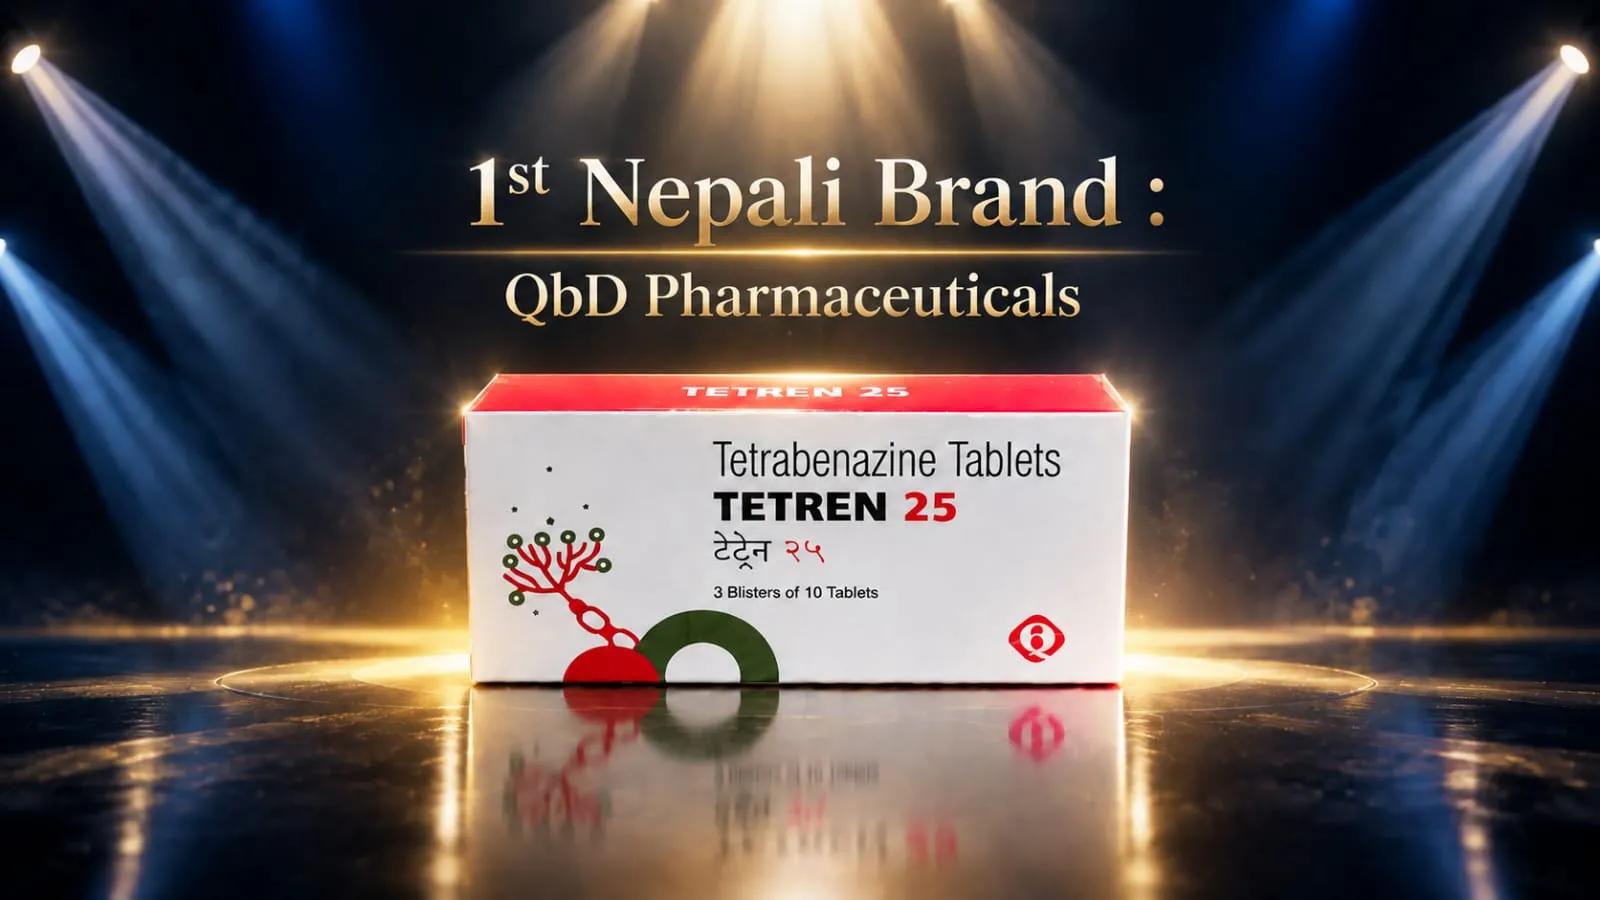
TETREN
Tetrabenazine
- Strength
- 25 mg
- Dosage form
- Tablets
- Pack size
- 3*10
- Packing
- Blister
Product information
PRESENTATION
Dosage Form: Tablet
Strength: 25 mg
Generic Name: Tetrabenazine
Pack Size: 3*10
Packing: Blister
CLINICAL PARTICULARS
Therapeutic Indications
Indicated for the treatment of chorea associated with Huntington’s disease.
To control of chorea, hemiballismus, tardive and buccolingual dyskinesias and certain dystonic syndromes.
DOSE AND METHOD OF ADMINISTRATION
Dosage
Adults
An initial dosage in adults of 25 mg twice a day is recommended. This can be increased by 25 mg a day every 3 or 4 days until the desired therapeutic effect is achieved, or until 200 mg/day is given, or unwanted side effects intervene.
Children
In children, 12.5 mg twice a day has been used as an initial dose with increments of
12.5 mg every 3 to 4 days until the desired therapeutic effect is obtained, or an upper limit
of 3 mg/kg/day is reached, or unwanted side effects intervene.
Dosage Adjustment
Dosage may need to be reduced in patients with impaired renal or hepatic function or in
elderly patients. It is reported that if no improvement is found after 7 to 10 days at the
maximum dose then it is unlikely that a higher dose or a longer duration of therapy will
benefit the patient.
CONTRAINDICATIONS
- Tetrabenazine should not be given closer than one day before or in combination with levodopa or reserpine as it blocks the action of these drugs, particularly the central action.
- Tetrabenazine should not be administered to people with a known sensitivity to tetrabenazine or to any of the excipients.
- Tetrabenazine should not be given to patients with Parkinsonism or depression, as it may worsen these conditions. It should not be administered within two weeks of treatment with a monoamine oxidase inhibitor (MAOI).
- Tetrabenazine is contraindicated during breast-feeding.
SPECIAL WARNINGS AND PRECAUTIONS FOR USE
Identified Precautions
As for other CNS active drugs, the effect of combination of tetrabenazine and other central
depressants including alcohol should be considered. Tetrabenazine may potentiate the action
of antihypertensive drugs.
Depression
Tetrabenazine may cause depression or worsen pre-existing depression. Cases of suicide ideation and behavior have been reported in patients taking the product. Caution should be exercised in treating patients with a history of depression or prior suicide attempts or ideation.
If depression or suicidal ideation occurs it should be controlled by reducing the dose and/or initiating antidepressant therapy. If depression or suicidal ideation is profound, or persists, discontinuation of tetrabenazine and initiation of antidepressant therapy should be considered.
MAOI antidepressants should not be used until at least two weeks have elapsed since the
last tetrabenazine dose, to avoid restlessness, disorientation and confusion, as well as a
potentially serious drug interaction resulting in hypertensive crisis.
Parkinsonism
Tetrabenazine can induce Parkinsonism and exacerbate pre-existing symptoms of
Parkinson’s disease. The tetrabenazine dose should be adjusted as clinically indicated to
minimize this side effect.
Neuroleptic Malignant Syndrome
Neuroleptic Malignant Syndrome is a rare complication of tetrabenazine therapy. Neuroleptic Malignant Syndrome most often occurs early in treatment or in response to changes in dose. The main symptoms of this condition are mental changes, rigidity, hyperthermia, autonomic dysfunction (sweating and fluctuations in blood pressure) and elevated creatinine phosphokinase levels. If Neuroleptic Malignant Syndrome is suspected tetrabenazine should be withdrawn immediately and appropriate treatment initiated.
QTc
Tetrabenazine causes a small increase (about 8 msec) in the corrected QT interval. In slow
metabolizers this increase may be greater (30msec). Tetrabenazine should be used with
caution with other drugs known to prolong QTc and in patients with congenital long QT
syndromes and a history of cardiac arrhythmias.
Dysphagia and Choking
Dysphagia and choking attacks with possibly consequent bronchopneumonia appear to be
the only acutely dangerous adverse effects of tetrabenazine reported so far. If these occur,
therapy should be discontinued.
Lactose
Patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency
or glucose-galactose malabsorption, should not take tetrabenazine tablets as they contain
lactose.
Orthostatic Hypotension
Tetrabenazine may induce postural hypotension at therapeutic doses and symptoms may
include postural dizziness and fainting. These should be considered in patients who may be
vulnerable to hypotension or its effects. Monitoring of vital signs on standing should be
considered in patients who are vulnerable to hypotension.
Use in Renal Impairment
The use of tetrabenazine in patients with renal insufficiency has not been studied.
Use in the Elderly
No specific studies have been performed in the elderly.
Pediatric Use
No adequately controlled clinical studies have been performed in children.
Effects on Laboratory Tests
There are no special requirements to monitor effects on laboratory tests.
INTERACTION
Interaction may occur when the following medications are administered with tetrabenazine
Reserpine and Levodopa:
Inhibit the action of these drugs and thereby attenuate their effects.
MAOIs:
Possible serious interactions resulting in hypertensive crisis. At least 14 days should
elapse between the discontinuation of MAOI and initiation of treatment with Tetrabenazine.
Tricyclic Antidepressants:
It has been reported to antagonize the locomotor activity induced by Tetrabenazine in
animals.
CNS Stimulants and Depressants:
Possible additive sedative effects should be considered when used in conjunction with
CNS depressants (including alcohol, neuroleptics, hypnotics and opioids).
Neuroleptic Agents:
Potential for significant dopamine depletion when administering with neuroleptic agents
e.g. haloperidol, chlorpromazine and metoclopramide. Patients should be monitored
clinically for the development of Parkinsonism. Neuroleptic malignant syndrome has
been observed in isolated cases.
Antihypertensives:
May increase risk of orthostatic hypotension.
Beta-blockers:
May increase risk of orthostatic hypotension.
CYP2D6 inhibitors:
In vitro and in vivo studies indicate that tetrabenazine and its metabolites, α- and βdihydotetrabenazine and are substrates for CYP2D6. β-HTBZ was also an inhibitor of
CYP2D6 at clinically relevant concentrations. Caution should be used when adding a
CYP2D6 inhibitor (such as fluoxetine, paroxetine, quinidine, duloxetine, terbinafine,
amiodarone, or sertraline) to a patient already receiving a stable dose of tetrabenazine,
or if the dose is influenced by the patient’s CYP2D6 metabolizer status. A reduction in
the dose of tetrabenazine should be considered.
Antipsychotics, antibiotics and Class IA and III antiarrhythmic medications:
Tetrabenazine causes a small increase (about 8 msec) in the corrected QT interval.
FERTILITY, PREGNANCY AND LACTATION
Effects on Fertility
There is no data available on the potential of tetrabenazine to affect fertility.
Use in Pregnancy - Category B3 (TGA)
- Category C (FDA)
There is inadequate evidence of safety of the drug in human pregnancy, and the potential
risk to humans is unknown. Tetrabenazine crosses the placenta and, because of the lack of
data and tetrabenazine should not be used during pregnancy. In the developmental toxicity tests, there was no evidence of utero mortality, growth retardation or teratogenicity either
rats or rabbits at oral doses up to 5 and 27 times the clinical dose based on body surface
area. When tetrabenazine was administered orally to female rats from the beginning of
organogenesis to weaning, an increase in stillbirths and postnatal mortality was observed
from 15 mg/kg/day, while delayed development was seen at 30 mg/kg/day. The no-effect
dose for neonatal effects (5 mg/kg/day) was approximately equivalent to the clinical dose
based on body surface area. The relative contributions of in utero and neonatal exposure and
Postnatal maternal neglect to these effects is unclear.
Use in Lactation
Tetrabenazine is excreted in milk. Oral administration to rats from early gestation to
weaning was associated with increased stillbirths, hypothermia and neonatal mortality in
pups (15 mg/kg/day, twice the clinical dose based on body surface area), and delayed pup
development (30 mg/kg/day, 5-fold the clinical dose). The relative contributions of in utero
and neonatal exposure and postnatal maternal neglect to these effects are unclear.
Tetrabenazine is contraindicated during breast-feeding.
EFFECTS ON ABILITY TO DRIVE AND USE MACHINES
As drowsiness may occur in up to 20% of patients, caution should be used when driving or
operating machines until competence to do so under treatment has been established. It might
be possible to reduce the drowsiness by careful dosage adjustment, especially initially.
ADVERSE EFFECTS (UNDESIRABLE EFFECTS)
Side effects include drowsiness, depression (which has on occasion been reported to be
associated with suicidal ideation and behavior) and Parkinsonism. The most commonly
reported side effects are as follows:
Central And Peripheral Nervous System Disorders:
Drowsiness (20%)
Parkinsonism (2 to 12%) at higher doses (may
include balancing problems, tremors or excess salivation)
Psychiatric Disorders:
Depression (6 to 10%)
Agitation (2.7%)
Anxiety (2 to 9%)
Insomnia (2 to 9%)
Confusion (1%)
Gastrointestinal System Disorders:
Dysphagia and choking attacks (4%) with
possibly consequent bronchopneumonia.
PRECAUTIONS FOR USE
Respiratory Disorders:
Bronchopneumonia
Central And Peripheral Nervous System Disorders:
Ataxia
Akathisia
Dizziness
Dyskinetic seizures
Dystonia
Memory impairment
Neuroleptic malignant syndrome (<0.01%)
Gastrointestinal System Disorders:
Nausea
Anorexia
Dryness of the mouth
Sialorrhea
Constipation
Diarrhea
Vomiting
Epigastric pain
Dysphagia
Psychiatric Disorders:
Disorientation
Feelings of unreality
Restlessness
Nervousness
Sleep disorders
Worsening aggression
General Disorders:
Lassitude
Hypothermia
Weight gain
Weaknesses
Fatigue
Cardiovascular Disorders:
Postural hypotension (1%)
Hypertensive crisis
Heart Rate and Rhythm Disorders: Bradycardia
Reproduction Disorders:
Irregular menstrual cycle
Skin And Subcutaneous Tissue Disorders
Sweating
Skin rash
Blood and lymphatic systems disorders
Leucopenia
Eye disorders
Oculogyric crisis
Photophobia
Metabolism and Nutrition Disorders Increased Appetite
Neuroleptic malignant syndrome (NMS) associated with the use of tetrabenazine has been
reported rarely. This may occur soon after initiation of therapy, following an increase in
dosage or after prolonged treatment. The main symptoms are mental changes, rigidity,
hyperthermia, autonomic dysfunction and elevated creatinine phosphokinase levels. If NMS
is suspected tetrabenazine should be withdrawn and appropriate supportive therapy instituted; treatment with dantrolene and bromocriptine may be effective.
OVERDOSE
Signs and symptoms of overdosage may include nausea, vomiting, diarrhea, confusion,
hallucinations, sedation, drowsiness, sweating, hypotension and hypothermia.
Management should be supportive. There is no information available on the effect of
pharmacological antagonists or dialysis.
PHARMACOLOGICAL PROPERTIES
Pharmacodynamic Properties
Mechanism of Action
Tetrabenazine is a synthetic derivative of benzyl quinolizine that causes depletion of
dopamine and other monoamines in the central nervous system.
Studies conducted in vitro have shown that tetrabenazine is an inhibitor of monoamine
transportation into pre-synaptic neuronal vesicles, by inhibition of VMAT2 (vesicular
monamine transporter 2), which is principally located in the central nervous system.
Dihydrotetrabenazine, the principal metabolite of tetrabenazine, has a similar affinity and
more significant selectivity for VMAT2, and both compounds are believed to contribute to
the pharmacological effect.
At a synaptic level tetrabenazine creates a reversible depletion of monamines in the
presynaptic vesicles. Animal studies have shown that tetrabenazine causes preferential
depletion of dopamine from nerve terminals in the CNS but neurotransmitter depletion by
a single dose of tetrabenazine is reversible and lasts only a few hours. This pharmacological
effect explains the therapeutic benefit of tetrabenazine in patients’ suffering from
hyperkinetic movement disorders.
PHARMACOKINETIC PROPERTIES
Absorption
Based on metabolite levels, tetrabenazine is quickly and mostly absorbed after oral
administration. Its absorption is not affected by the taking of food. After administration of
single doses from 12.5 to 50mg of tetrabenazine, for the metabolites alpha and beta
dihydrotetrabenazine, the maximum plasma concentration and the area under the curve
increased approximately in proportion to the dose, indicating a linear kinetic. Clinical
testing has shown that a single oral dose of tetrabenazine undergoes extensive (>75%)
absorption from the gastro-intestinal tract.
Metabolism
The metabolism of tetrabenazine is complex, initially proceeding via the formation of alpha
and beta dihydrotetrabenazine. The majority of the observed metabolites appear to be
formed from these dihydrotetrabenazines because of O-dealkylation, hydroxylation and
conjugation. No significant build-up has been observed after daily administration. The
elimination half-life of dihydrotetrabenazine is approximately 5 to 6 hours.
Excretion
Tetrabenazine is mostly eliminated in metabolised form in urine.
PRECLINICAL SAFETY DATA
Genotoxicity
Tetrabenazine and its major metabolites, α- and β-dihydrotetrabenazine, were negative in
the in vitro bacterial reverse mutation assay. Tetrabenazine was clastogenic in the in vitro
chromosome aberration assay in Chinese hamster ovary cells in the presence of metabolic
activation, while α- and β-dihydrotetrabenazine were clastogenic in Chinese hamster lung
cells in the presence and absence of metabolic activation. In vivo micronucleus tests in rats
and mice with tetrabenazine were negative. The genotoxic potential of tetrabenazine is
considered to be low.
Carcinogenicity
A 6-month study in transgenic p53(+/-) heterozygous mice and a long-term study in male
rats at oral doses up to 30 mg/kg/day and 6 mg/kg twice daily, respectively, did not
provide any evidence of carcinogenic potential. These doses correspond to exposures
approximately 3 to 4 times the clinical exposure, based on plasma AUC or dose based on
body surface area. Mammary gland hyperplasia was observed in female rats that received
twice daily oral doses of 7.5 mg/kg or greater for 6 months associated with exposures
(plasma AUC) like clinical exposure. As the effect of tetrabenazine on prolactin
levels are not known, the relevance of this finding is uncertain.
STORAGE
Store below 30°C. Store in original container. Keep out of reach of children.